BIBF 1120 (Nintedanib) Targets Receptor Tyrosine Kinases to Attenuate Idiopathic Pulmonary Fibrosis
Copy code to add this image to your page
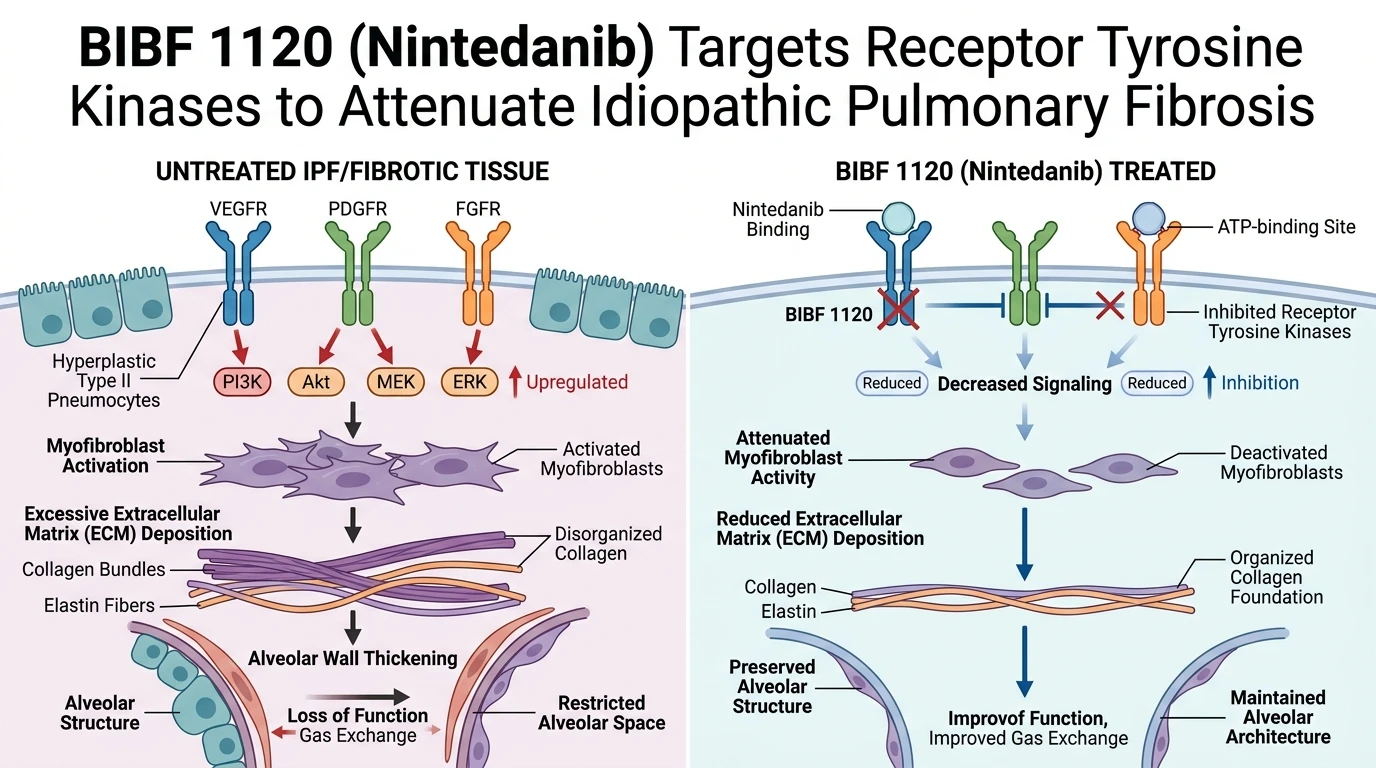
Target engagement of BIBF 1120 (Nintedanib) occurs through competitive inhibition of the ATP-binding pocket across distinct receptor tyrosine kinase (RTK) families. Specifically, the molecule targets platelet-derived growth factor receptors (PDGFR-α and PDGFR-β), fibroblast growth factor receptors (FGFR1, FGFR2, and FGFR3), and vascular endothelial growth factor receptors (VEGFR1, VEGFR2, and VEGFR3). In human lung fibroblasts under in vitro conditions, enzymatic assay panels demonstrate nanomolar half-maximal inhibitory concentrations (IC50) ranging between 13 and 200 nmol/L for these primary targets. Ligand-induced receptor autophosphorylation is consequently blocked, halting signal transmission through downstream Ras-Raf-MEK-ERK and PI3K-AKT intracellular cascades.
Pathological pulmonary remodeling in idiopathic pulmonary fibrosis (IPF) relies on sustained signaling through these growth factor pathways. Activated fibroblasts migrate to damaged alveolar structures and transdifferentiate into alpha-smooth muscle actin-positive myofibroblasts. These specialized effector cells synthesize and secrete excess extracellular matrix components, predominantly type I collagen and fibronectin. Additionally, indirect cross-talk with transforming growth factor-beta (TGF-β) pathways amplifies local fibrotic reactions. In preclinical rodent models of bleomycin-induced pulmonary fibrosis—frequently generated using specialized gene delivery methods such as adeno-associated virus delivery systems—administration of the compound significantly attenuated collagen accumulation and parenchymal tissue stiffness.
At the cellular level, kinase selectivity profiling reveals high specificity for the catalytic clefts of PDGFR, FGFR, and VEGFR over non-receptor tyrosine kinases like Src or Abl, as well as serine/threonine kinases. Binding kinetics reveal a slow dissociation rate from the active catalytic domain of PDGFR-β, ensuring prolonged kinase inhibition even during transient fluctuations in systemic drug concentration. Cellular phenotyping assays demonstrate that this sustained target occupancy attenuates fibroblast chemotaxis toward recombinant PDGF-BB ligands and blocks extracellular matrix contraction in three-dimensional collagen gel matrices. Furthermore, microvascular endothelial cell tube formation assays indicate concurrent suppression of angiogenic sprouting driven by VEGF-A and FGF-2. These dual antifibrotic and anti-angiogenic mechanisms jointly normalize the local microenvironmental niche within diseased pulmonary parenchyma.
Translational characterization progressed through rigorous clinical evaluations, starting with the randomized Phase II TOMORROW trial. This study established that a dosage of 150 mg twice daily achieved optimal pharmacodynamic activity while maintaining an acceptable clinical safety profile. Subsequent pivotal Phase III trials (INPULSIS-1 and INPULSIS-2) evaluated this dose in 1,061 total patients diagnosed with IPF across 24 countries. The primary endpoint across both INPULSIS trials was the annual rate of decline in forced vital capacity (FVC). In INPULSIS-1, the adjusted annual rate of FVC decline was -114.7 mL per year in the treatment arm compared to -239.9 mL per year in the placebo arm. Similarly, INPULSIS-2 demonstrated an annual FVC decline of -113.6 mL per year versus -207.3 mL per year for placebo controls.
Subgroup analyses from these trials confirmed that the therapeutic effect remained consistent across diverse baseline clinical patient profiles. Benefit was demonstrated regardless of baseline impairment in forced vital capacity, baseline radiological pattern on high-resolution computed tomography (such as honeycombing vs non-honeycombing patterns), or concomitant emphysema. Time to first acute exacerbation was also significantly delayed in pooled analyses from the INPULSIS studies, providing evidence that target engagement modifies acute clinical destabilization events alongside chronic disease progression.
Safety profiles evaluated during pivotal trials established a manageable adverse event profile dominated by gastrointestinal effects. Diarrhea occurred in approximately 62% of trial participants receiving active therapy compared to 18% in placebo groups, though less than 5% of patients discontinued treatment due to this symptom. Transaminase elevations occurred in a minority of subjects, necessitating routine monitoring of hepatic function parameters. Real-world observational cohorts and post-marketing registries confirm these clinical trial findings in unselected patient populations, including elderly patients presenting with significant cardiac or renal comorbidities. Furthermore, clinical observational studies indicate that treatment maintains patient stability while serving as a pharmacological bridge to lung transplantation in advanced disease stages.
Pharmacodynamic Profile and Clinical Efficacy Analysis
Copy code to add this image to your page
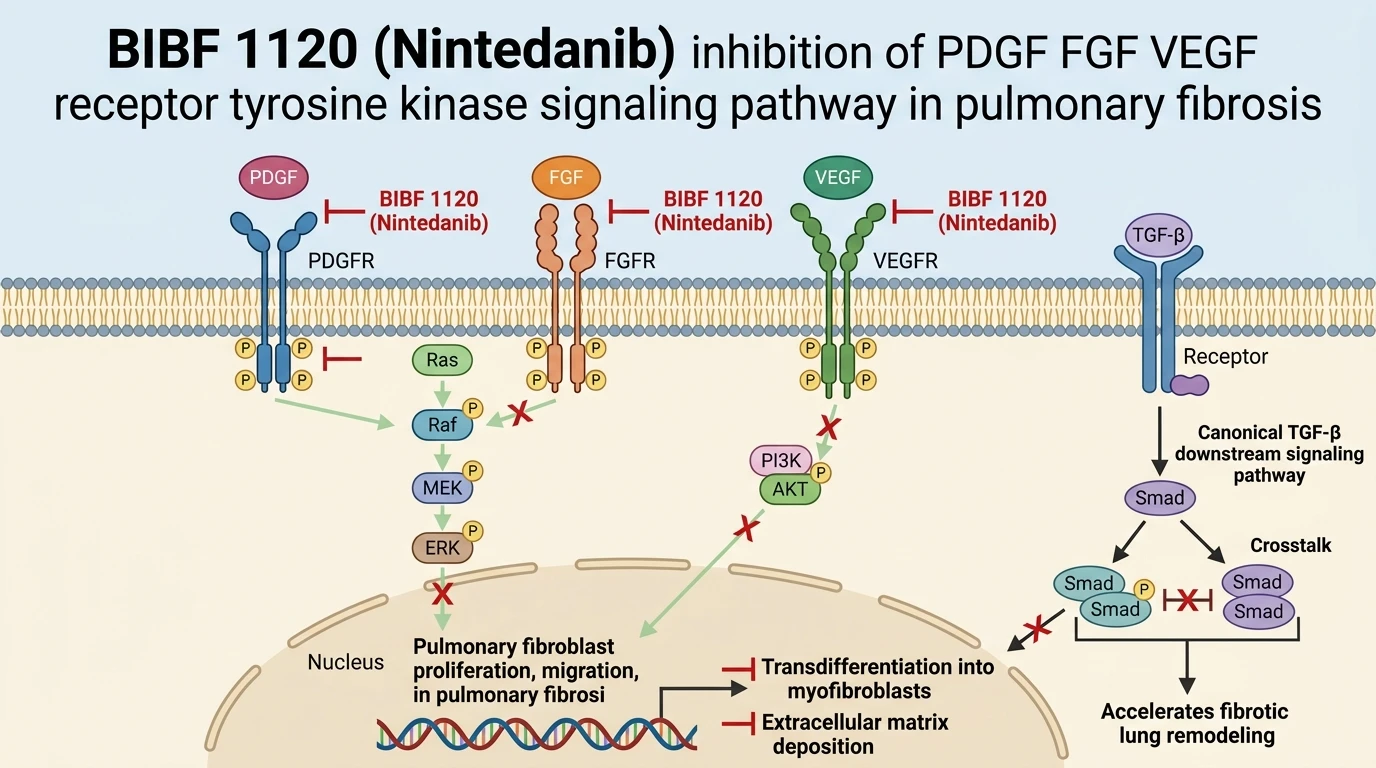
BIBF 1120 (Nintedanib) is an ATP-competitive small-molecule inhibitor targeting platelet-derived growth factor receptors (PDGFR α/β), fibroblast growth factor receptors (FGFR 1-3), and vascular endothelial growth factor receptors (VEGFR 1-3). By blocking ATP binding in the intracellular catalytic kinase cleft, the drug halts receptor autophosphorylation and suppresses downstream ERK and AKT intracellular cascades. This enzymatic blockade attenuates pulmonary fibroblast proliferation, migration, and transdifferentiation into active matrix-secreting myofibroblasts, resulting in slowed functional pulmonary decline in idiopathic pulmonary fibrosis.
Competitive ATP Binding Suppresses Downstream Kinase Cascades
The molecular architecture of BIBF 1120 enables high-affinity binding within the ATP-binding cleft of targeted receptor tyrosine kinases. Crystallographic analysis indicates an oxindole core structure that occupies the ATP cassette, forming key hydrogen bonds with the hinge region. ATP occupancy is effectively prevented. Intracellular signaling cascades collapse rapidly upon target binding. Downstream autophosphorylation of PDGFR and FGFR ceases within minutes of administration in primary human lung fibroblast assays. Consequently, phosphorylation of extracellular signal-regulated kinase (ERK1/2) drops by over 80% relative to untreated control cells. Fibroblast migration towards PDGF and FGF gradients decreases markedly under these conditions. Transdifferentiation into myofibroblasts is similarly impaired. Matrix metalloproteinase secretion shifts toward an anti-remodeling phenotype. Cellular viability in non-fibrotic lung parenchyma remains largely preserved during sustained exposure.
Attenuated Forced Vital Capacity Decline in IPF Patients
Clinical verification of receptor tyrosine kinase inhibition relies on long-term spirometric measurements. Pulmonary functional decline slows measurably in patients receiving BIBF 1120 therapy. Phase III data confirmed a relative reduction in annual FVC loss exceeding 50% compared to placebo controls. Acute exacerbation frequency also decreased in pooled clinical study analyses. Gastrointestinal tolerability remains the primary management consideration in clinical practice. Diarrhea symptoms typically manifest during the initial three months of administration. Dose adjustments or temporary interruptions successfully resolve mild to moderate gastrointestinal events in most patients. Hepatic transaminase levels require baseline and periodic monitoring during active therapy. Long-term observational registries confirm sustained safety in real-world clinical practice.